
The foot changes less than the person does
Structurally, adolescence is often quieter than the years before it. Relapse is mostly a younger child’s event. What changes is everything around the foot: a body growing fast, sport getting more serious, changing rooms, and a teenager who has started noticing that one calf is thinner. Most of what arrives in these years is not orthopedic.



The decade
Stage by stage
Ages are rough (children arrive at these at very different times). What holds is the order they come in.
The last big growth phase
The adolescent growth spurt is the final one that can pull on a treated foot, and it is worth a degree of attention for that reason. Tight tissue under a fast-lengthening bone behaves the same way it did at five, and a foot that has been stable for years can tighten noticeably over a few months.
The difference is that late relapse is far less common than early relapse, and it usually presents as stiffness and reduced dorsiflexion and not a foot visibly turning back in. Check that the foot still comes up past neutral with the knee straight. If it has quietly stopped doing so, that is worth an appointment even without pain.
Where the foot stops being a medical matter
Somewhere around fourteen, most teenagers with a treated clubfoot (congenital talipes equinovarus, or CTEV) stop thinking about it as a condition and start thinking about it as a feature of their body they did not choose. A thinner calf, a smaller foot, scars, buying shoes that fit one side properly. In a changing room, those things are considerably louder than they are in a clinic.
This is the part parents are least prepared for, because nothing has gone wrong medically. My own experience of that age was that I would have traded a good deal of function for a matching pair of calves, which is not a sentence any orthopedic follow-up ever asked me about. Asking a direct question about it (not about pain, about how they feel about it) is worth more than another range-of-motion check.
Decisions that outlast the decade
Sport gets more selective, physical jobs and services start being considered, and teenagers begin making choices about their own bodies. This is where good information does the most good, and where the two failure modes are equally costly.
One is a young person who has been told their foot is fine so many times that they push through a genuine problem for years. The other is one who has absorbed a story of fragility and rules out things they could comfortably have done. Both are avoidable with an honest, specific account of what their foot is and is not.
Mine was not the quiet decade, and this page would be dishonest if it only described the common version.
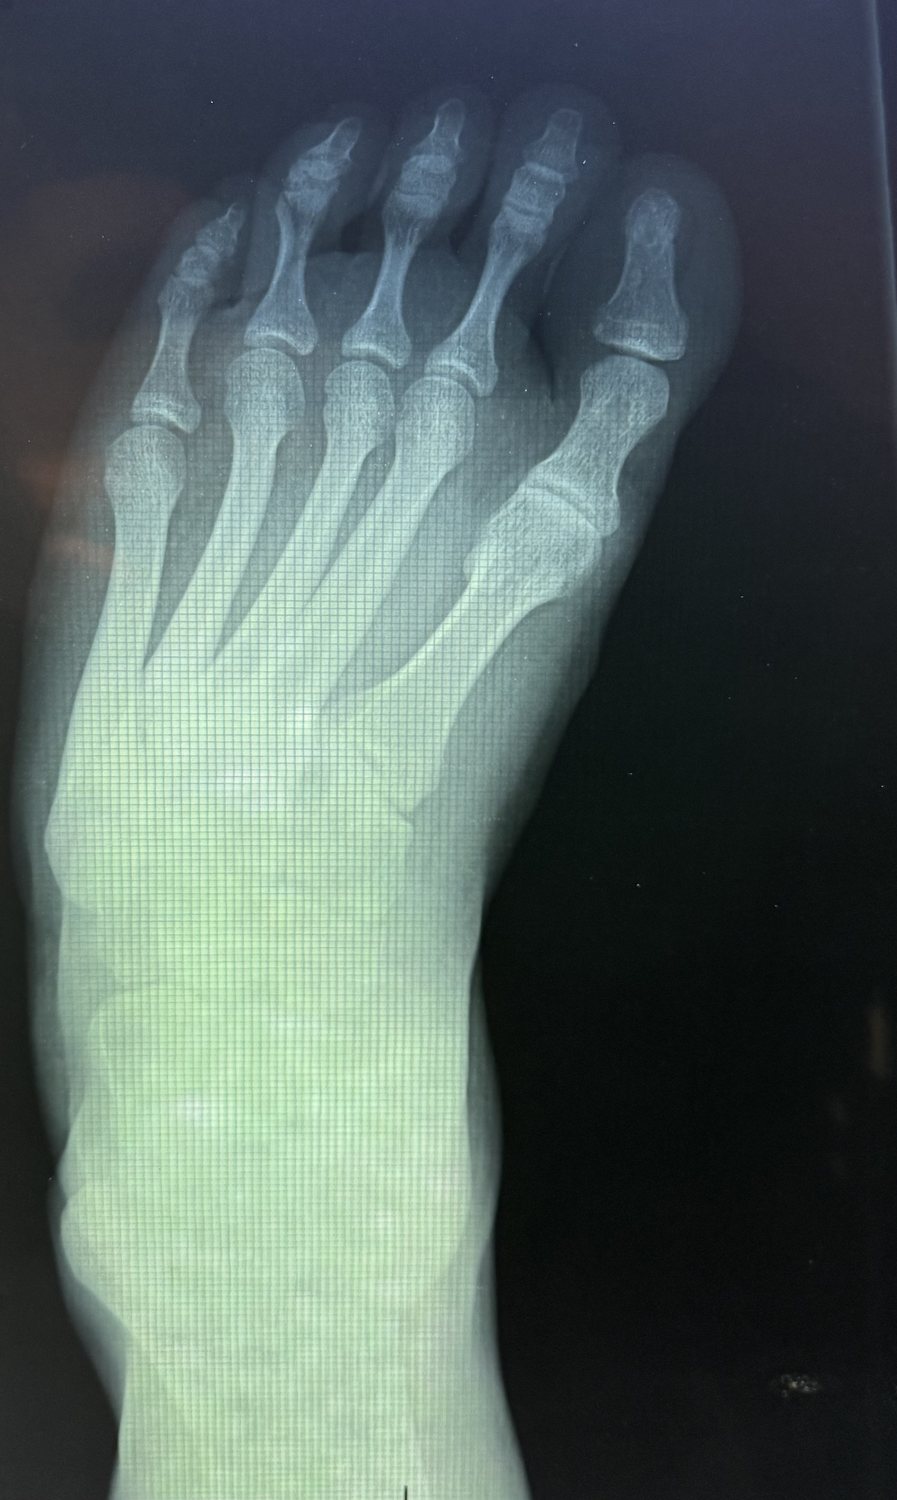
At fifteen the left foot had a prominent, painful bone on the outside border and I was walking on that border rather than across the sole. That October I broke the fourth metatarsal, recorded as a stress fracture rather than an impact one. The following March I hurt the same foot in a baseball game and went in that evening to have it X-rayed, because once you have broken a bone you assume you have broken it again. I still have those films. I do not know what they were read as, because whatever I was told that night is not written down anywhere I can reach. That same month I re-sprained the ankle and spent six weeks in a cast. The clinic note from that May reads like a list: hindfoot in varus, weight running down the lateral border, no weight going through the great toe at all, callus and redness along the outside, and beaking of one of the midfoot bones on the films. In August, at sixteen, the left hindfoot was fused, and I missed the first half of the football season of my junior year.
That sequence is not a forecast and I am not offering it as one. It is what the exception looks like from inside, and it is worth knowing the exception exists.
Handing over the file, and the story
Pediatric follow-up usually ends somewhere around sixteen to eighteen, and adult orthopedics does not automatically pick it up. A great many adults with clubfoot, myself included, spend decades with no specialist contact at all because nobody explicitly handed anything over.
Two things are worth doing before discharge. Get a copy of the records (operative notes, imaging, clinic letters) into your child’s own hands, because they become very hard to obtain later. And make sure they can describe their own history accurately: what was done, when, and what it left. That account is the thing they will be asked for at every appointment for the rest of their life.
I did this the wrong way round and it cost me twenty-three years. My pediatric file closed in March 2003, a few weeks before I turned eighteen, discharged to follow-up as needed. Nobody picked it up, and it did not occur to me to ask anyone to.
When I finally went looking in 2026, the records from my teenage years came back, because that was a large hospital with a records department and a legal duty. The infant surgery was somewhere else entirely, and those notes did not come from any hospital. They came from my mother, in a folder she had kept for forty-one years. Ten pages, including both operative notes. Without her I would still be guessing at what was actually done to both of my feet at four months old, and I would have spent the rest of my life describing my own history wrongly at appointments, which I had already been doing for decades without knowing it.
Records departments keep things for a while. Mothers keep things for longer. Do not rely on either.
What actually changes, and what does not
The calf difference deserves a specific mention because it causes disproportionate distress and is poorly explained to most families. It is partly structural, the muscle is genuinely smaller and always will be, and partly trainable. Strength responds well to work; size responds only a little. Being told that plainly is more useful at fifteen than being told it does not matter, because they can already see that it does.
Nobody is self-conscious about their dorsiflexion. They are self-conscious about their calf.

Signs still worth acting on
Adolescence being mostly quiet does not mean ignoring the foot. Four things warrant an appointment instead of observation: dorsiflexion that has reduced compared with a year ago, pain that is present most weeks, not after unusual activity, a change in how they walk that other people notice, and any activity given up because of the foot instead of because of interest.
That last one is the most easily missed. Teenagers rarely announce that something has become difficult; they let it drop and find a reason afterwards.
Sources
Where this comes from
People also ask