
Does clubfoot come back?
Yes, it can. And that is a known feature of the condition, not a sign that something went wrong, the entire second half of Ponseti treatment exists because of it.



Parents usually arrive at this question having noticed something: a foot turning in again, a heel that lifts, more toe-walking, a brace that suddenly fits worse. The word relapse is frightening because it sounds like starting over.
It rarely means that. But it is worth understanding why a foot that was fully corrected can drift, because that explains almost everything about how clubfoot (talipes equinovarus) is treated.
Why a corrected foot drifts
Casting realigns the foot. It does not remove whatever caused the foot to form that way in the first place, and that underlying tendency is still present in the tissue as the child grows.
So the corrected position is held, not permanent. Through years of growth, tight structures can gradually pull back toward the original pattern. Slowly, quietly, and usually without any single moment where something happens.
This is the reason bracing lasts years and not months. It is not caution. It is the tendency that is still there.
What relapse actually looks like
Not a dramatic reversal. A cluster of small mechanical changes that keep pointing the same direction.
How these present changes considerably with age. A baby in boots shows different signs from a nine-year-old on a soccer field. That is covered page by age in relapse signs by age. And whether what you are seeing is relapse at all, instead of an ordinary stiff spell, is the whole subject of normal tightness vs relapse.
Is it the brace, or the foot?
The one distinction that sorts most worries. Five questions about what you are seeing, answered for the last two weeks.
What changed
Which of these is closer to what is happening?
Usually fit, growth, illness or routine. Fixable, and common.
That points at the foot, not the brace.
How long
Is it one bad day, or repeating?
One day on its own is noise.
A repeat across two weeks is a pattern.
At rest
Is the front of the foot turning inward again when relaxed?
Good.
One of the recognized signs.
The ankle
Does the foot come up less at the ankle than it did?
Good.
Worth asking the clinic to check at the next visit.
One of the recognized signs.
Walking
If walking, is there more toe-walking after a period of flat walking?
Skip this one.
Good.
One of the recognized signs, especially if it is on the treated side.
A child fighting the boots is usually a child fighting the boots. A foot that resists going into a boot that fitted last month is a different conversation.
What treating it usually involves
| Caught | Typically involves |
|---|---|
| Early | A short course of repeat casting, and a reset of the bracing schedule. Often a few weeks. |
| Later | Repeat casting plus a further tenotomy, or a tendon transfer, depending on age and stiffness. |
| Late, stiff | More extensive surgical options, because the foot has lost the flexibility that made casting work. |
Read that table as an argument for calling early and not as a set of outcomes. The same relapse sits in the top row or the bottom row depending mostly on how long it went unnoticed.
For scale
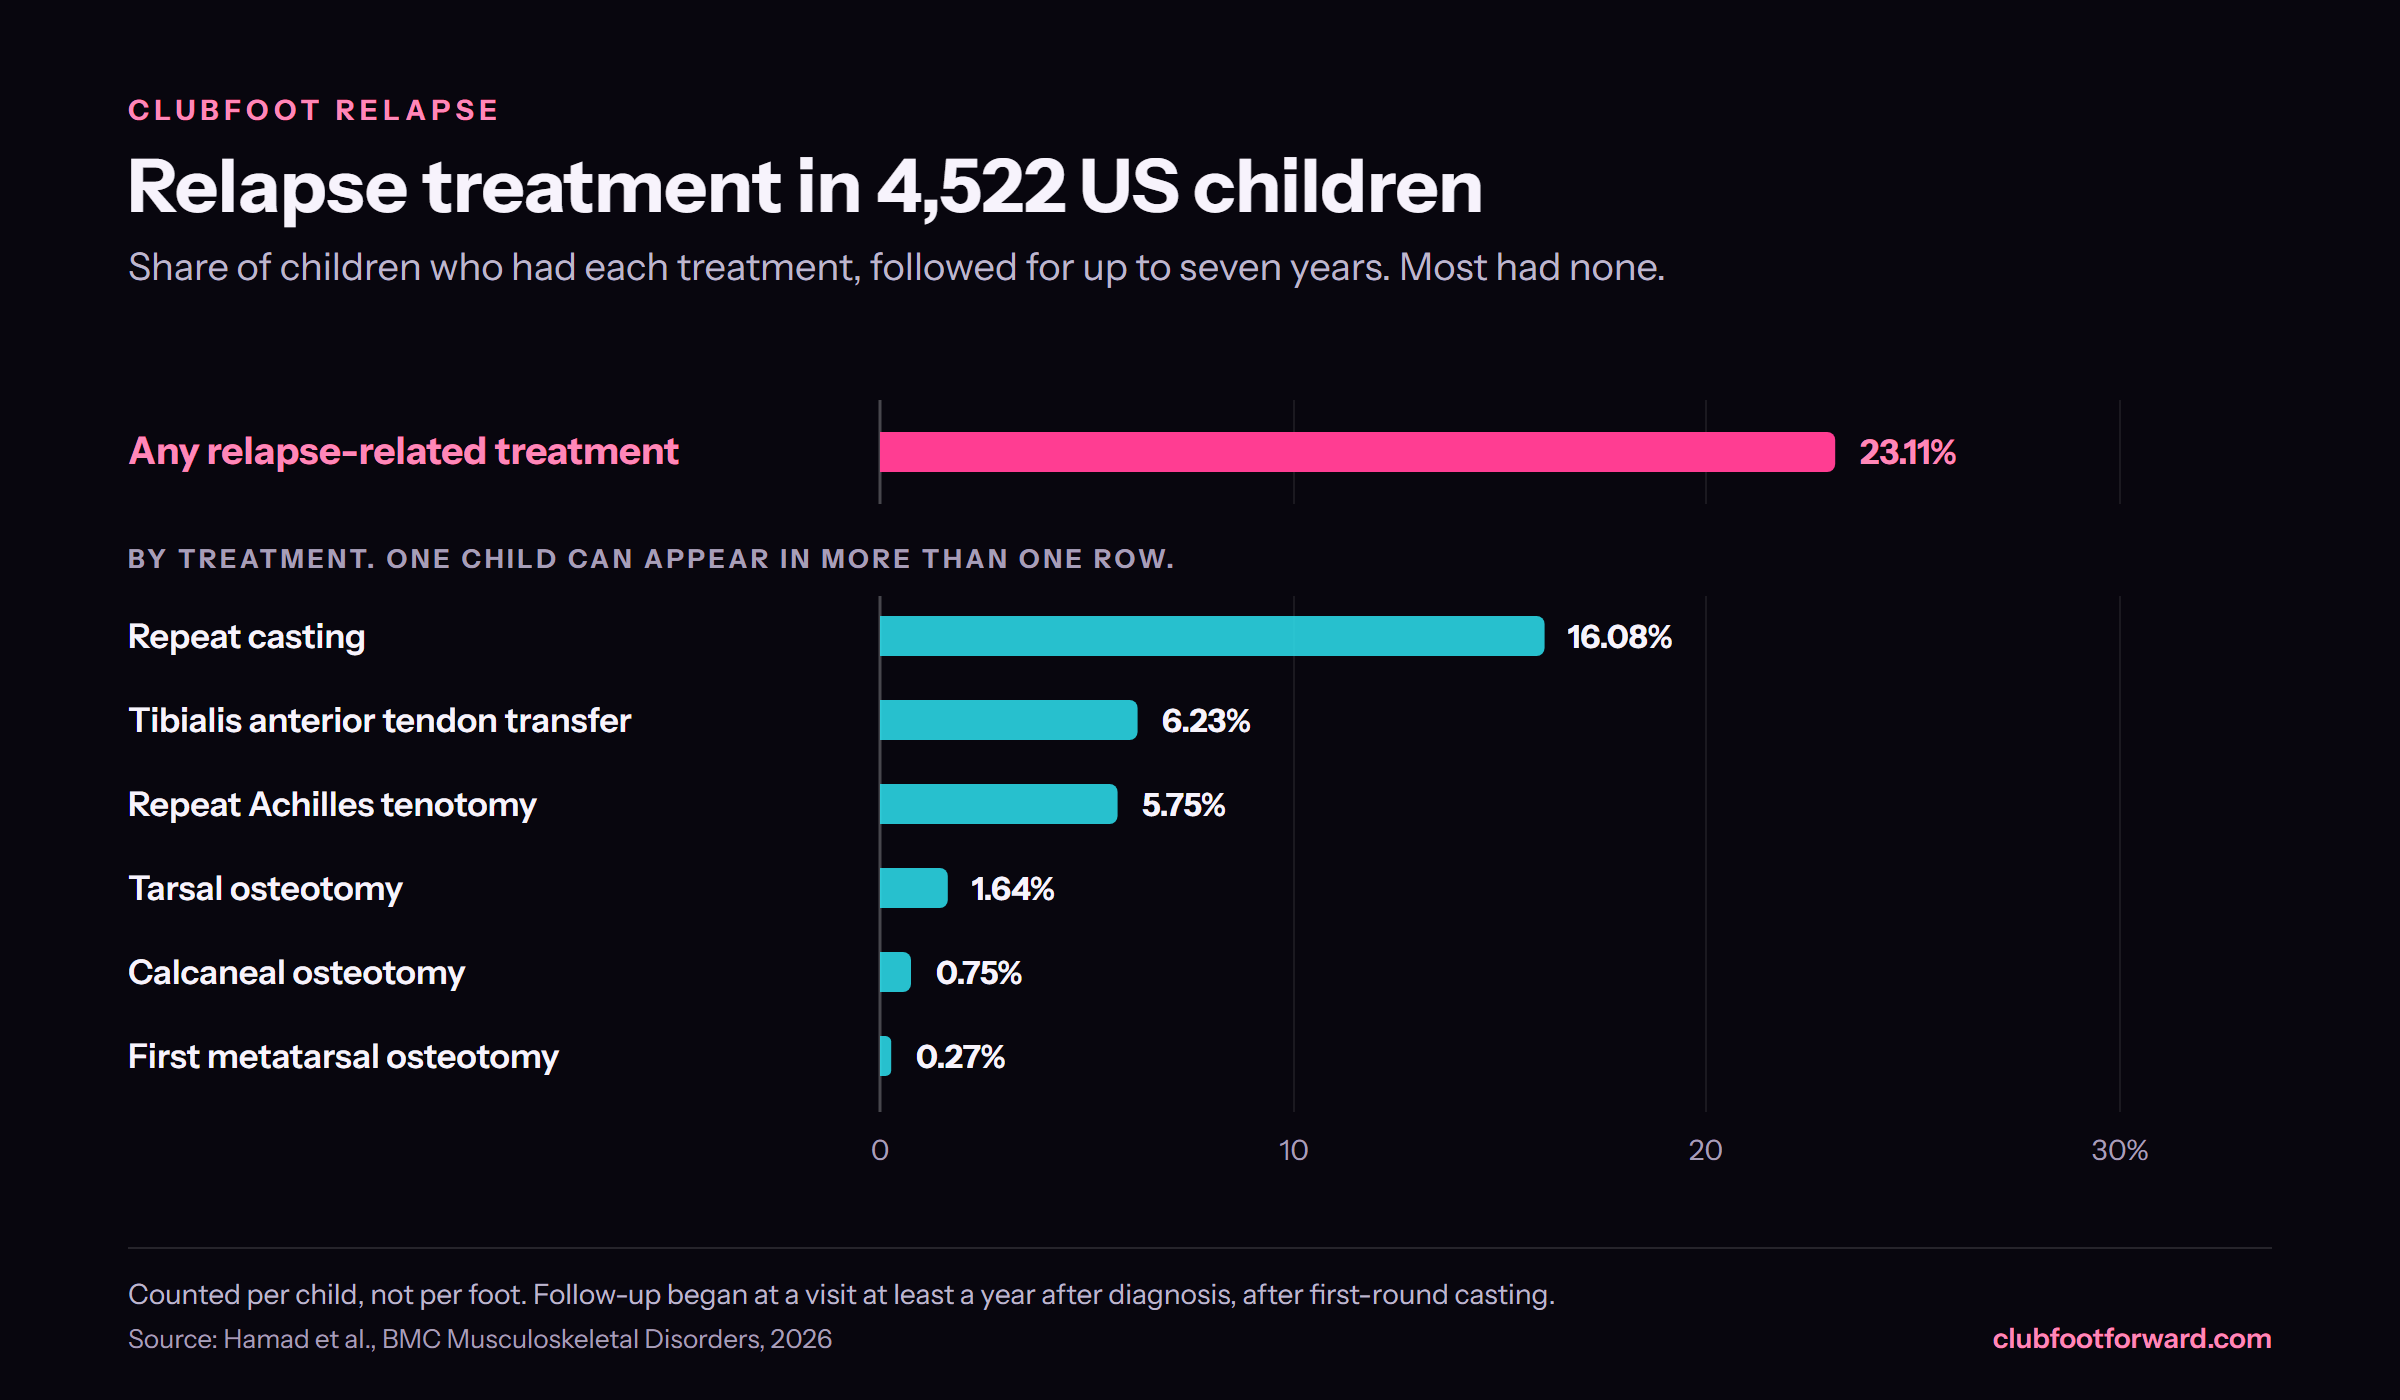
How often each treatment is actually used
Across 4,522 US children diagnosed with idiopathic clubfoot in their first year and followed for up to seven years, 23.11 percent had some relapse-related treatment. Repeat casting was the most common, at 16.08 percent. A tibialis anterior tendon transfer was done in 6.23 percent and a repeat Achilles tenotomy in 5.75 percent. Bone operations were uncommon: a tarsal osteotomy in 1.64 percent, a calcaneal osteotomy in 0.75 and a first metatarsal osteotomy in 0.27. A child can count toward more than one of those, which is why they add up to more than 23 percent.9
A separate 2026 review pooling studies worldwide put relapse at around one child in four.10 The two figures measure slightly different things, one counting treatments and the other relapses, and both land in the same range.
Relapse is not a failure, and it is not yours
Brace adherence lowers the risk substantially. It does not eliminate it. Some feet relapse with everything done exactly right, particularly syndromic and neuromuscular clubfoot, and the honest framing is that this is a condition with a recurrence tendency, not a treatment anyone got wrong.
I am the plainest example of that I know. Both of my feet had the same release, in the same operation, when I was four months old. My left foot relapsed and was operated on again at two years and ten months. My right foot never needed it. Same child, same operation, same day.
Nobody has ever told me why one held and the other did not, and I do not think anyone could. I was treated in the surgical era, before Ponseti casting was standard, so my feet are not a forecast for a baby in boots today. They are just proof that two feet treated identically can go two different ways, with nobody at fault.
People also ask
Relapse and recurrence
Does clubfoot relapse after treatment?
Why does a corrected foot come back?
Does relapse mean surgery?
How common is it?
Is relapse the parents’ fault?
Can it be treated successfully?
Why does a corrected clubfoot come back?
When is clubfoot most likely to relapse?
How common is clubfoot relapse?
Can relapse happen years after treatment?
Can clubfoot relapse be treated successfully?
Sources